
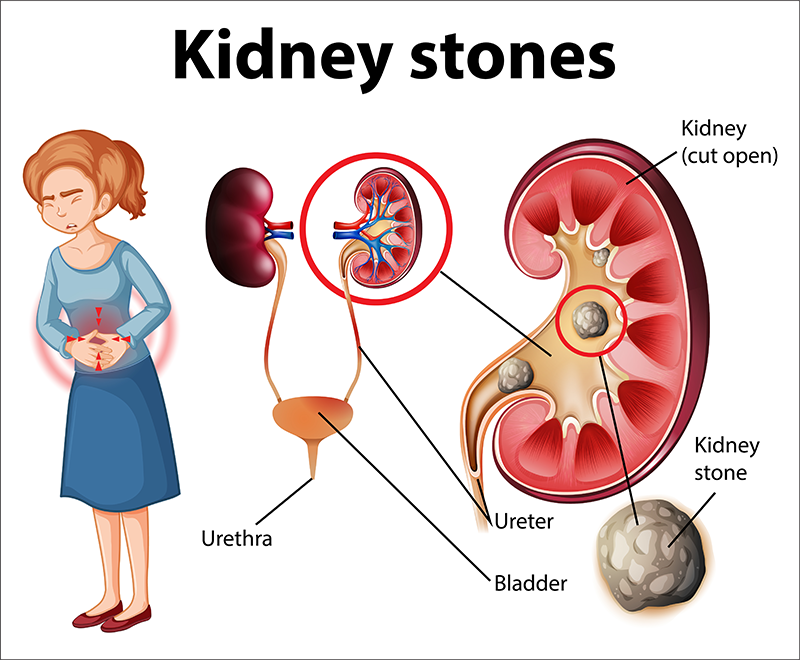
Retrograde intrarenal surgery, or RIRS, is an endoscopic procedure used to treat selected stones inside the kidney. A thin, flexible telescope passes through the urinary passage to reach the stone, which is usually broken into smaller pieces using a laser.
RIRS generally avoids a skin incision, but it remains an invasive procedure with anaesthesia requirements and possible complications. Its suitability depends on the stone, urinary anatomy and the person’s overall health.
Understanding its benefits alongside its limitations can help patients participate in treatment decisions.
RIRS is a form of flexible ureteroscopy used within the kidney.
The telescope passes through the:
The surgeon views the stone through the telescope. Laser energy fragments it, and some pieces may be removed using a small basket. Other fragments may pass later in urine.
For general background, read about kidney and ureteric stones.
Who May Be Considered for RIRS?
RIRS may be discussed when a kidney stone requires treatment and flexible ureteroscopy is an appropriate approach.
Relevant considerations include:
Not every kidney stone requires surgery. Observation or another treatment may be more appropriate.
For larger renal stones, particularly those over 2 cm, percutaneous nephrolithotomy—PCNL—is generally the first-line treatment. RIRS may still be considered in selected circumstances, with discussion of staged treatment and its limitations.
RIRS reaches the kidney through the urinary tract, usually without creating a wound through the skin. This distinguishes it from procedures that access the kidney through the back.
Avoiding a skin incision does not mean there will be no discomfort or internal tissue injury.
The flexible telescope allows the surgeon to locate stones and treat them under vision. Its flexibility helps reach different parts of the kidney, although anatomy can limit access.
A laser can break stones into smaller fragments for removal or passage. The outcome depends on factors such as stone burden, composition and location.
Complete clearance in one session cannot be guaranteed. Residual fragments may require monitoring or additional treatment.
Selected patients may go home on the day of treatment or after an overnight stay. Others need longer observation because of symptoms, infection risk or the complexity of the procedure.
Discharge and recovery should follow clinical findings rather than a promised timeline.
Potential complications include:
If the ureter is too narrow, the surgeon may place a temporary stent and arrange treatment later rather than force access.
The consent discussion should explain which risks are particularly relevant to the individual.
A ureteric stent is a thin tube placed between the kidney and bladder to support urine drainage.
It may be used before or after RIRS, depending on access, swelling, injury or other findings. Not everyone needs the same stent plan.
Possible stent symptoms include:
Confirm when and how the stent will be removed or exchanged. Do not assume that it will dissolve or come out without a plan.
Preparation may include review of imaging, urine testing, kidney function and fitness for anaesthesia.
Tell the treating team about all medicines, supplements, allergies and previous anaesthetic problems. Follow their fasting instructions and advice about blood-thinning or diabetes medicines.
Do not stop prescribed medicines independently.
An infection may need treatment before stone removal. When infection occurs with an obstructed kidney, urgent drainage and infection treatment may take priority over definitive stone surgery.
Temporary burning, mild bleeding and discomfort can occur after ureteroscopy. A stent may contribute to symptoms.
Follow the discharge plan for pain relief, fluid intake, activity and medicines. Fluid advice should account for any existing medical restrictions.
Return to work, driving and exercise depends on recovery, the procedure and the medicines being taken. Follow-up may include imaging to assess remaining fragments or drainage.
Seek urgent medical assessment after RIRS for:
Do not dismiss fever as an expected stent symptom.
| Option | What it involves | Important consideration |
|---|---|---|
| Observation | Monitoring selected stones. | Requires an appropriate follow-up plan. |
| Shock wave lithotripsy | External shock waves fragment the stone. | Suitability depends on stone and patient factors. |
| RIRS | A flexible telescope reaches the kidney through the urinary tract. | May require a stent or staged procedures. |
| PCNL | Instruments reach the kidney through a tract in the back. | Often preferred for larger or complex renal stones. |
These options are not interchangeable. The recommended approach should reflect expected clearance, risks, anatomy and patient preferences.
RIRS treats existing stones; it does not remove every reason stones form.
Prevention may involve stone analysis, dietary advice, an individual fluid plan and selected blood or urine investigations. Some patients also need medicines.
Follow-up remains relevant even when treatment has cleared the original stone.
No. It usually avoids a skin incision, but instruments enter the urinary tract. Anaesthesia and procedural risks still apply.
No. Suitability depends on stone size, location, anatomy, infection, kidney function and other factors.
Not always. Larger or multiple stones, difficult access and safety considerations may mean treatment is staged.
Possibly. The decision depends on findings before and during surgery. Confirm the removal or exchange plan if one is placed.
Anaesthesia is used during treatment, but discomfort can occur afterwards, particularly with a stent. Pain management should follow the treating team’s instructions.
Recovery varies. The timing depends on symptoms, work demands, medicines and the procedure performed.
Yes. New stones may form if underlying risk factors remain. Prevention and follow-up should be tailored to the individual.
RIRS provides an endoscopic option for treating selected kidney stones through the urinary passage. Its potential benefits include direct stone viewing and laser fragmentation without a skin incision.
These benefits must be balanced against infection, ureteric injury, stent symptoms and the possibility of further treatment. An informed decision includes alternatives, expected recovery and follow-up.
Further procedural information is available on the RIRS information page.
Medical disclaimer: This article provides general educational information and does not replace personalised medical advice, diagnosis or treatment. Procedure selection, preparation and recovery require individual clinical assessment.
Plot no 70, Moreshwar Heritage, Sector 5, Ulwe, Navi Mumbai, Maharashtra 410206
For Booking: +91 8591009591
Chat With Us
49, Sion – Panvel Hwy, Sector 7, Vashi, Navi Mumbai, Maharashtra 400703
For Booking: +91 8007542142
Chat With Us