
A slow or weak urine stream is a common complaint among men, especially after age 40. It can feel like you have to strain to start urinating, that the flow stops and starts, or that your bladder never empties completely. While the symptom itself is simple, the underlying causes are varied and require accurate diagnosis. In this article we compare the two most frequent culprits—benign prostatic hyperplasia (BPH) and urethral stricture—so you can understand the signs, the tests, and the treatment paths.
When the urinary tract is partially blocked, the bladder must generate higher pressure to push urine through. This results in a stream that is slower, weaker, or intermittent. According to clinical overviews of weak urine streams, men often notice additional symptoms such as:
The prostate surrounds the urethra just below the bladder. As men age, the gland can enlarge and compress the urethra, reducing the caliber of the passage. This is the most common reason for a weak stream in men over 40. Research shows that an enlarged prostate often presents with a slow urine flow and can also cause urgency and frequency.
A urethral stricture is a narrowing of the urethra caused by scar tissue. Scarring can result from infections, pelvic trauma, or medical procedures that involve catheters or endoscopic instruments. Urethral stricture causes include sexually transmitted infections, previous prostate surgery, and even radiation therapy.
Less common reasons for a weak stream include certain medications (anticholinergics, alpha‑blockers), bladder neck obstruction, and neurological conditions such as multiple sclerosis. While these are not the primary focus of this article, they may coexist with BPH or stricture.
The urologist will ask about the onset, duration, and pattern of symptoms, as well as any history of urinary infections, surgeries, or trauma. A digital rectal exam (DRE) can estimate prostate size and feel for irregularities.

Key investigations include:
These tests are discussed in depth on our common urology problems page, which also outlines when to seek urgent care.
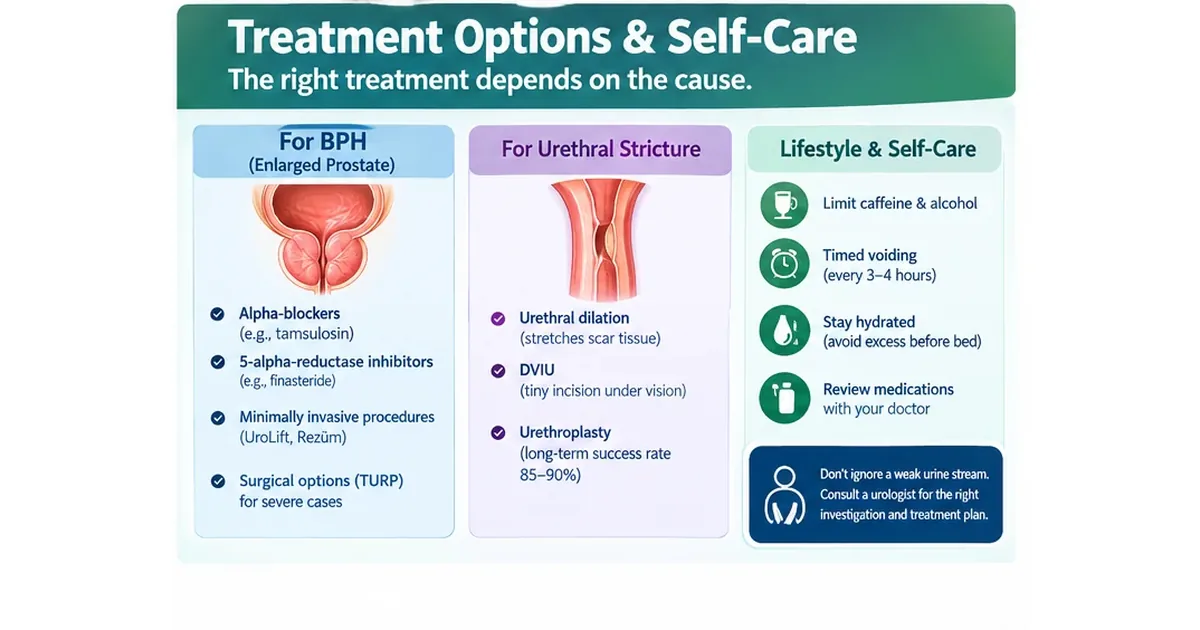
Therapies aim to relax the prostate’s smooth muscle or shrink the gland:
Stricture management focuses on restoring urethral diameter:
For detailed guidance on stricture treatment, see the article on urethral stricture symptoms and care.
Regardless of the diagnosis, certain habits can ease symptoms:
Our urine health guide provides additional tips for maintaining optimal bladder function.
Typical BPH signs include a gradual slowdown in flow, difficulty starting urination, frequent nighttime trips, and a feeling that the bladder isn’t empty after voiding.
Urethral strictures often cause a sudden change in stream strength, intermittent flow, and may be accompanied by a history of urinary infections, catheter use, or pelvic trauma.
While most cases involve BPH or stricture, a persistent weak stream should be evaluated because prostate cancer or bladder tumors can also cause obstruction.
Yes—reducing caffeine and alcohol, staying well‑hydrated, and practicing timed voiding can lessen irritation and improve flow, but they don’t replace medical treatment for underlying blockages.
Urethroplasty has a long‑term success rate of 85‑90 % for longer or recurrent strictures, making it the preferred option when dilation or DVIU fails.
Alpha‑blockers may cause dizziness or low blood pressure, while 5‑alpha‑reductase inhibitors can lead to reduced libido; your doctor will balance benefits and risks.
If you notice a persistently weak urine stream, schedule a urology appointment promptly. Accurate testing will reveal whether BPH, a urethral stricture, or another factor is responsible, allowing you to pursue the most effective treatment and regain comfortable urination.
Plot no 70, Moreshwar Heritage, Sector 5, Ulwe, Navi Mumbai, Maharashtra 410206
For Booking: +91 8591009591
Chat With Us
49, Sion – Panvel Hwy, Sector 7, Vashi, Navi Mumbai, Maharashtra 400703
For Booking: +91 8007542142
Chat With Us